Decoding the White Coats and Scrubs: Who Does What on Your Hospital Care Team

From the moment you are admitted, a procession of professionals in scrubs and white coats moves through your room. Some check machines, some ask long lists of questions, some seem to make decisions while others carry them out. For patients and families, it can be genuinely confusing — and that confusion has a cost. When you don't know who to ask, important questions go unasked.
Here is a working map of the people most likely to be involved in your care, and how to use each of them well.
The Hospitalist: Your On-Site Quarterback
If you are admitted to a medical unit, the physician overseeing your care is often a hospitalist — a doctor who specializes exclusively in treating hospitalized patients. Unlike the physician who knows your history from years of appointments, the hospitalist knows the inside of a hospital cold, and coordinates everything that happens during your stay.
Ask the hospitalist about: your diagnosis and treatment plan, what each test is for, and what the goals are for discharge. Expect a daily visit; if rounds happen while you're asleep, ask the nurse when the doctor typically comes by.
Registered Nurses (RNs): Your Constant
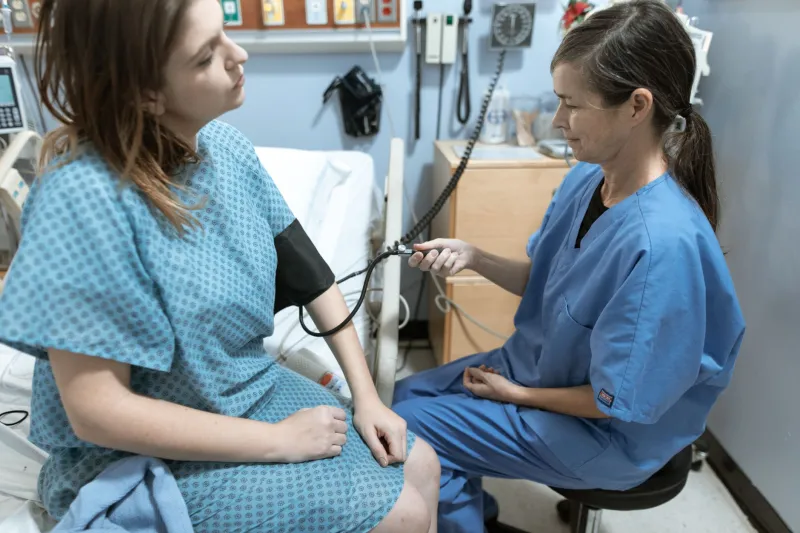
RNs are the people you will see most, and they are far more than medication deliverers. They monitor your condition around the clock, administer treatments, manage pain, and — critically — notice changes first. If your breathing changes overnight or your pain control isn't working, your nurse is both the first to see it and the fastest route to a physician.
Ask your RN about: symptoms you're experiencing, medication timing, wound care instructions, and anything that feels wrong. Describe changes specifically: "the pain moved from my side to my chest" is more actionable than "I don't feel great."
LPNs and Nursing Assistants: The Hands-On Layer
Licensed practical nurses and nursing assistants handle much of the direct, personal care — vital signs, bathing, repositioning, feeding assistance. They are not the right person for clinical questions, but they are your eyes-and-ears allies. Be candid with them about pain, mobility, and comfort; what they observe gets charted and passed to the RN.
Nurse Practitioners and Physician Assistants: The Mid-Level Clinicians
NPs and PAs hold graduate-level clinical training and can diagnose, order tests, and prescribe — often in collaboration with a physician. On many units, you may see an NP or PA more often than the attending physician, particularly for daily progress checks.
Ask an NP or PA about: test results, medication changes, and day-to-day clinical decisions. They frequently have more time for detailed conversation than the physician on rounds.
Specialists: The Focused Experts
If your condition involves a specific system — a cardiologist for the heart, a nephrologist for the kidneys — a specialist will weigh in. They typically see you briefly and advise the hospitalist rather than directing your overall care.
Ask specialists about: their specific findings and recommendations. Save broad questions about your overall plan for the hospitalist, who sees the whole picture.
The Case Manager: Your Exit Strategist
Among the least understood roles, and among the most important. Case managers — often nurses or social workers — arrange what happens after you leave: home health, rehab placement, medical equipment, insurance authorizations, and follow-up appointments.
Ask the case manager about: discharge logistics, insurance coverage for post-hospital care, and community resources. Raise concerns early; arranging equipment and coverage takes days, and the day before discharge is often too late.
The Patient Advocate: Your Escalation Path
Nearly every hospital employs patient advocates or representatives whose job is to resolve problems — communication breakdowns, billing disputes, complaints about care. If something is troubling you and the clinical team hasn't resolved it, this is the person to call. Asking for the patient advocate is not an act of hostility; it is using the system as designed.
Making the Team Work for You
Three habits keep your concerns from falling through the cracks:
Keep a running list. Jot questions as they occur to you and raise them at the next visit rather than trying to remember at the moment.
Name a family spokesperson. With multiple relatives asking different staff different questions, information fragments. One designated point person who joins rounds keeps communication coherent.
Repeat back what you heard. "So the plan is to switch my antibiotic tomorrow and reassess — is that right?" This simple habit catches misunderstandings before they become errors.
Hospitals are teams, not lone practitioners — and the system works best when you know which teammate handles what. Don't hesitate to ask, "Who should I talk to about this?" It is a question every member of your care team expects, and it is one of the most useful things a patient can say.